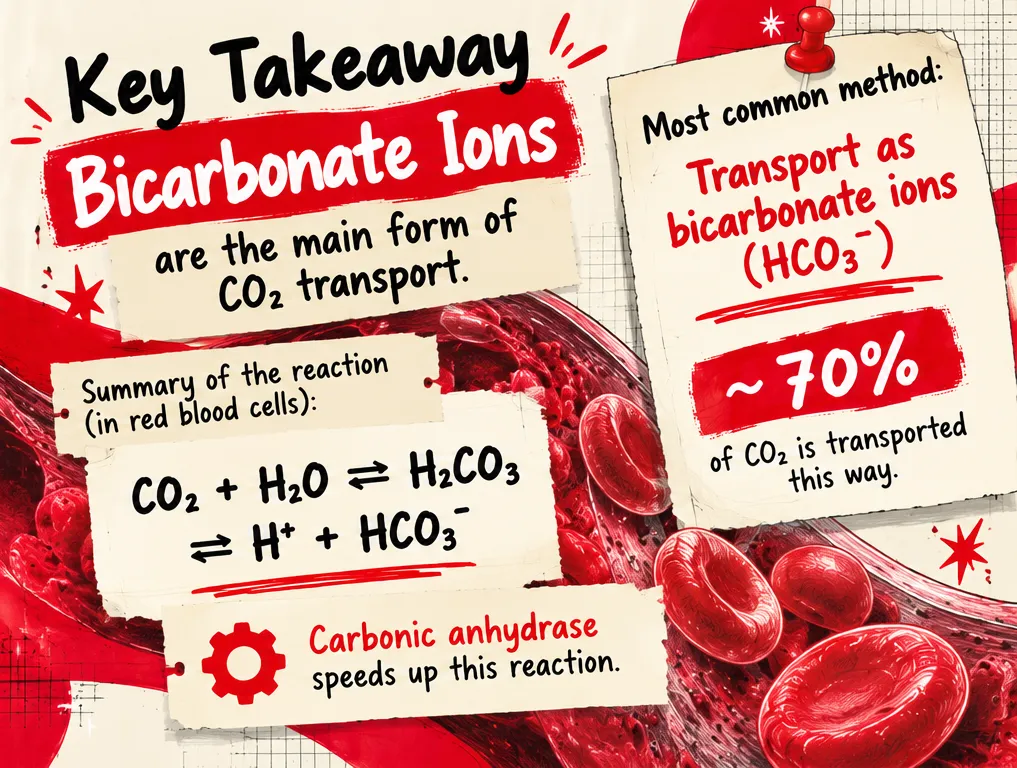
How is carbon dioxide transported in the blood? In three ways. About 70% travels as bicarbonate (hydrogencarbonate) ions, which makes this the most common method. Roughly 20–23% is attached to haemoglobin as carbaminohaemoglobin, and about 7–10% simply dissolves in the plasma. All three routes carry carbon dioxide from the body's cells to the lungs, where it is breathed out.
Where does the carbon dioxide come from?
Every living cell in your body releases energy by cellular respiration. In aerobic respiration, glucose is broken down using oxygen, and carbon dioxide is one of the waste products. Most of it is made in the mitochondria, the tiny structures where the later stages of respiration take place.
A waste gas that keeps building up would be a problem. Carbon dioxide dissolves in water to make an acid, so too much of it would upset the chemistry of every cell. The blood therefore has to collect it from the tissues and carry it to the lungs, all the time. It is the second half of the gas exchange story: oxygen travels in towards the cells, and carbon dioxide travels out.
The first step is simple. Carbon dioxide moves out of the cells and into the blood by diffusion, because its concentration (its partial pressure) is higher in the respiring tissues than in the blood that arrives there. Once it has crossed the wall of a capillary, it enters the plasma, and from the plasma most of it moves on into the red blood cells.
The three forms of carbon dioxide transport at a glance
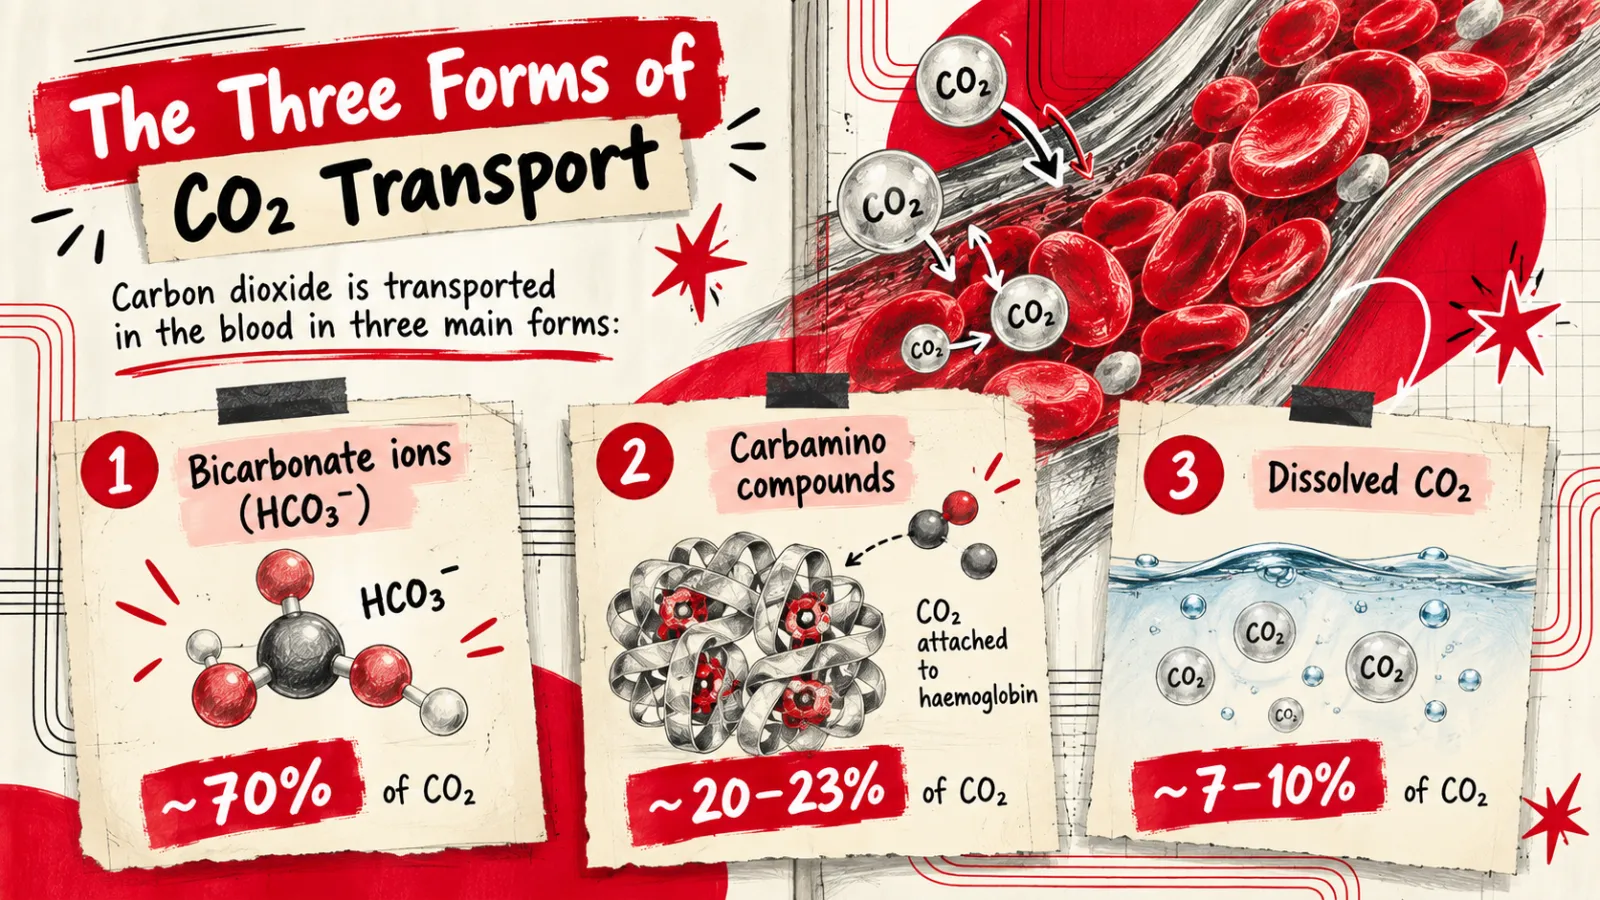
Carbon dioxide is not carried in just one way because no single method could cope with the amount the body makes. Different forms do different jobs, so it helps to meet them side by side before looking at each one.
| Form | Share of the CO₂ in blood | Where it is carried | Key idea |
|---|---|---|---|
| Bicarbonate ions (HCO₃⁻) | About 70% | Mostly in the plasma, after being made inside red blood cells | CO₂ reacts with water; the enzyme carbonic anhydrase speeds it up |
| Carbaminohaemoglobin | About 20–23% | Inside red blood cells | CO₂ binds to the globin part of haemoglobin, not to the iron |
| Dissolved CO₂ | About 7–10% | Plasma | CO₂ is not very soluble, so only a small share travels this way |
Different textbooks give slightly different figures. OpenStax Anatomy and Physiology gives about 70%, about 20% and 7–10%, while other references quote 70%, 23% and 7%. They all agree on the order: bicarbonate first, then carbaminohaemoglobin, then dissolved gas. For an exam, learn the ranges above and say "approximately".

The journey in five steps
Before the chemistry, here is the whole trip in outline. Follow the numbers and you have the skeleton of almost every exam answer on this topic.
- Cells make carbon dioxide in aerobic respiration.
- CO₂ diffuses out of the cells, through the tissue fluid and into the blood in a capillary.
- Most of the CO₂ enters red blood cells, where it is converted to bicarbonate ions or attached to haemoglobin. A small part stays dissolved in the plasma.
- The circulatory system carries the blood back to the heart and then to the lungs.
- In the lung capillaries the reactions run backwards, CO₂ is released, diffuses into the alveoli and leaves the body when you breathe out.
Notice how much of this is reversible. The same reactions that load carbon dioxide onto the blood in the tissues unload it in the lungs. Which direction they run depends on the partial pressure of carbon dioxide, high in the tissues and low in the alveoli. That single idea will come back again and again below.
Why can't blood just carry CO₂ as a dissolved gas?
It is a fair question, because dissolving is the simplest way to carry a gas. The trouble is that carbon dioxide is not very soluble in blood. If dissolved gas were the only method, blood would need to flow far faster, or the body would have to put up with much higher levels of carbon dioxide, to shift the same amount.
Chemical conversion gets round this limit. When CO₂ is converted into bicarbonate ions, it stops counting as dissolved gas, so the plasma can take up more of it. In the same way, once CO₂ is attached to haemoglobin it no longer adds to the pressure of free carbon dioxide. Both tricks keep the partial pressure of dissolved CO₂ low, which lets more carbon dioxide diffuse into the blood from the tissues. Your blood is carrying far more carbon dioxide than plain solubility would allow.
Red blood cells do most of the work
Red blood cells (erythrocytes), described in more detail in our human blood lesson, are best known for carrying oxygen, but they are central to carbon dioxide transport too. Three features make them ideal:
- They contain haemoglobin. This protein carries oxygen on its iron-containing haem groups and also picks up CO₂ and hydrogen ions on other parts of the molecule.
- They contain carbonic anhydrase. This enzyme greatly speeds up the reaction between CO₂ and water. It is found inside red blood cells, not in the plasma.
- They have a huge surface area. Their biconcave shape and tiny size let gases move in and out quickly.


Mature red blood cells have no nucleus, which leaves more room for haemoglobin. Each cell is packed with haemoglobin, so the whole population of red cells makes a very large "carrier fleet" for both gases.
Why does the form of carbon dioxide matter?
You might wonder why biology courses make you learn three separate forms. The answer is that each one helps in a different way. Bicarbonate carries the bulk of the carbon dioxide. Carbaminohaemoglobin is a smaller store, but a very responsive one that is strongly affected by oxygen levels, as you will see in the section on the Haldane effect. Dissolved carbon dioxide is small in amount, yet it is the form that actually diffuses across membranes and sets the pressure that drives every other step.
Next, we take the biggest share, bicarbonate, apart reaction by reaction.
Form 1: bicarbonate ions, the most common method
Bicarbonate is the star of this topic. About 70% of the carbon dioxide that diffuses into the blood is carried to the lungs this way. The name is a shortcut: the ion HCO₃⁻ is formally called the hydrogencarbonate ion, and UK exam boards use either name.
Step by step: how bicarbonate forms
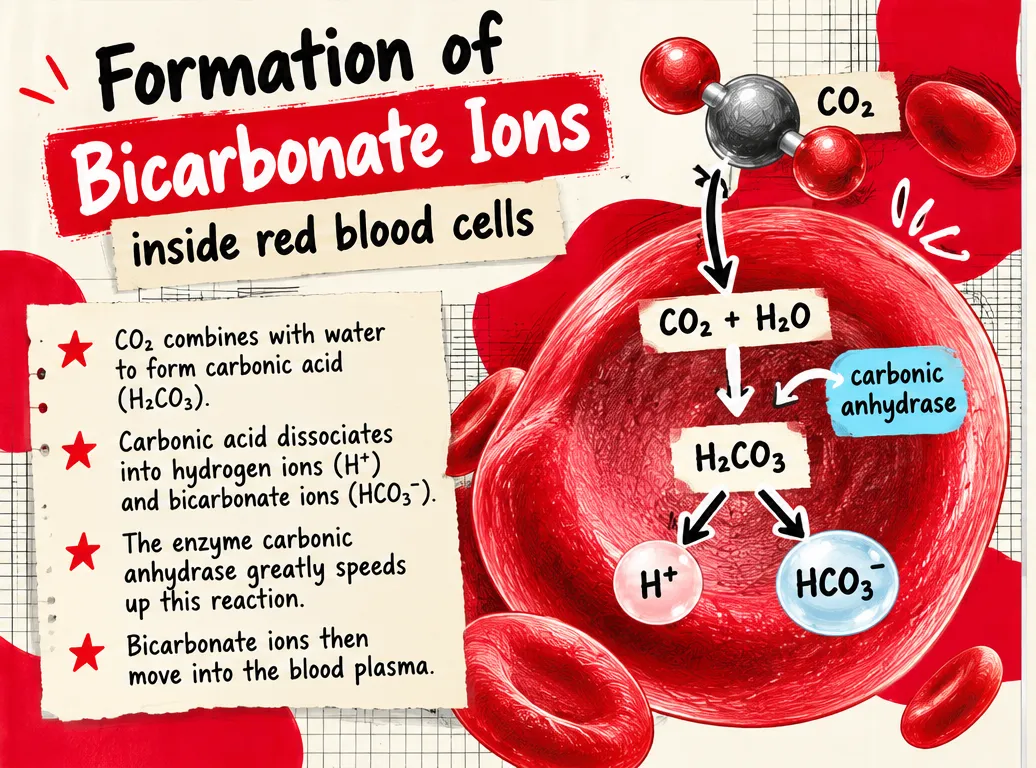
Most bicarbonate is made inside red blood cells. Here is the sequence:
- Carbon dioxide diffuses from the plasma into a red blood cell.
- Inside the cell, CO₂ combines with water to form carbonic acid (H₂CO₃).
- Carbonic acid immediately splits into a hydrogen ion (H⁺) and a hydrogencarbonate ion (HCO₃⁻).
- The bicarbonate ions leave the red cell and move into the plasma. The hydrogen ions stay behind and are mopped up by haemoglobin.
As a single reversible equation:
CO₂ + H₂O ⇌ H₂CO₃ ⇌ H⁺ + HCO₃⁻
Without help, carbon dioxide reacts with water slowly. That is where the enzyme comes in.
Carbonic anhydrase: the enzyme that makes it fast
Carbonic anhydrase is an enzyme found inside red blood cells. It catalyses the first step, CO₂ + H₂O ⇌ H₂CO₃, so that carbon dioxide can be converted quickly while the blood is still passing through the capillaries. The second step, the splitting of carbonic acid into ions, needs no enzyme.
Plasma lacks this enzyme. That is why the conversion happens mainly in the red cells, and why those cells are so important for carbon dioxide transport as well as for oxygen.
Enzymes do not decide which way a reversible reaction goes. They only make it reach equilibrium faster. In the tissues, the partial pressure of CO₂ is high, so the reaction runs to the right and makes bicarbonate. In the lungs, the partial pressure is low, so the same enzyme speeds up the reaction in the opposite direction.
The chloride shift (Hamburger shift)
As bicarbonate builds up inside a red blood cell, its concentration becomes higher there than in the plasma outside. Bicarbonate therefore leaves the cell, moving down its concentration gradient into the plasma. But a red cell cannot just lose negative charge without something in return, or the cell and the blood would become electrically unbalanced.
The solution is an exchange. For each bicarbonate ion that leaves, a chloride ion (Cl⁻) enters through a carrier protein in the membrane. One negative ion swaps for another, so the charge stays balanced. This is the chloride shift, also called the Hamburger shift or Hamburger phenomenon after Hartog Jakob Hamburger.
A neat consequence is that the plasma in venous blood contains slightly less chloride than the plasma in arterial blood, because chloride has moved into the red cells on the way.
Haemoglobin as a buffer for hydrogen ions
Making bicarbonate also makes hydrogen ions, and free hydrogen ions would make the blood more acidic. The red cell deals with this in two ways. First, the hydrogen ions are held inside the cell instead of leaving. Second, haemoglobin acts as a buffer by binding them.
Deoxygenated haemoglobin, the form found in the tissues after oxygen has been delivered, is a better acceptor of hydrogen ions than oxyhaemoglobin. So the tissues, where oxygen has just been released, are exactly where haemoglobin is best at mopping up the acid made when carbon dioxide arrives. Everything slots together in a rather elegant way.
Why is bicarbonate the main method?
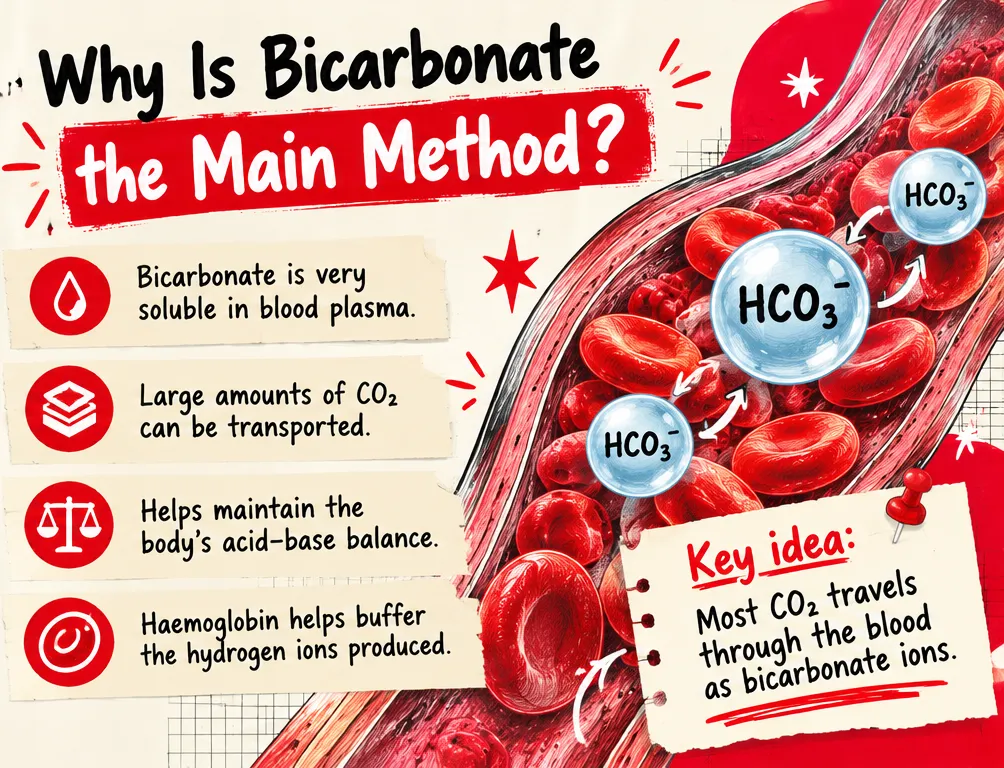
Several reasons add up:
- It is soluble. Bicarbonate dissolves easily in plasma, unlike carbon dioxide gas.
- Large amounts can be carried. Converting CO₂ into ions removes it from the pool of dissolved gas, so more can diffuse in from the tissues.
- It supports acid–base balance. Bicarbonate is the main part of the blood's buffer system, which keeps the pH steady. In blood of normal pH there is roughly 20 times more bicarbonate than carbonic acid.
- It is easily reversed. The reactions run backwards in the lungs, releasing carbon dioxide where it is needed.
Form 2: carbaminohaemoglobin
The second route is a direct attachment. About 20–23% of the carbon dioxide in blood binds to haemoglobin inside red blood cells, forming carbaminohaemoglobin (carbaminohemoglobin in American spelling).
Here is a point that catches many students out. Oxygen attaches to the iron atom in the haem group. Carbon dioxide does not. Instead, CO₂ attaches to amino groups on the globin protein chains. The two gases therefore bind to different parts of haemoglobin.
Hb + CO₂ ⇌ HbCO₂
The reaction is reversible and depends on the partial pressure of carbon dioxide. Where it is high (the tissues), more CO₂ binds. Where it is low (the lungs), CO₂ comes off and diffuses into the alveoli.
Deoxygenated haemoglobin binds CO₂ much more readily than oxygenated haemoglobin. In fact, one reference puts the capacity of deoxygenated haemoglobin at about 3.5 times that of oxyhaemoglobin. This is the heart of the Haldane effect, which we meet in the next part.
Form 3: dissolved carbon dioxide
The last form is the simplest. A small fraction, about 7–10%, of the carbon dioxide that enters the blood simply dissolves in the plasma and is carried as CO₂ molecules. When the blood reaches the lungs, this dissolved gas diffuses across the respiratory membrane into the alveoli.
Although it is the smallest share, dissolved CO₂ matters out of proportion to its size. It is the form that diffuses across membranes, so its partial pressure drives every exchange between tissues, blood and lungs. The other forms act as reservoirs that keep this pressure low enough for more CO₂ to keep entering the blood.
Test your recall: trace the path
Name the three forms in which CO₂ is transported in blood and give the approximate share of each. (3 marks)
Hydrogencarbonate (bicarbonate) ions, about 70%; carbaminohaemoglobin, about 20–23%; dissolved CO₂ in plasma, about 7–10%.
Explain the role of carbonic anhydrase in CO₂ transport. (2 marks)
It is an enzyme in red blood cells that catalyses the reaction between CO₂ and water to form carbonic acid, which splits into H⁺ and HCO₃⁻, so CO₂ is converted to bicarbonate quickly enough for transport.
What is the chloride shift and why does it happen? (2 marks)
Bicarbonate ions leave red blood cells in exchange for chloride ions entering. It keeps the electrical charge balanced across the red cell membrane.
Where does CO₂ bind to haemoglobin, and how is this different from oxygen? (2 marks)
CO₂ binds to amino groups on the globin chains to form carbaminohaemoglobin. Oxygen binds to the iron in the haem groups.
What happens in the lungs?
After the heart pumps it to the lungs (see the cardiac cycle for how), the blood meets the air, and everything runs in reverse. The air in the alveoli contains much less carbon dioxide than the blood in the surrounding capillaries, so the partial pressure of CO₂ is now higher in the blood than in the air. That gradient pulls carbon dioxide out of the blood.
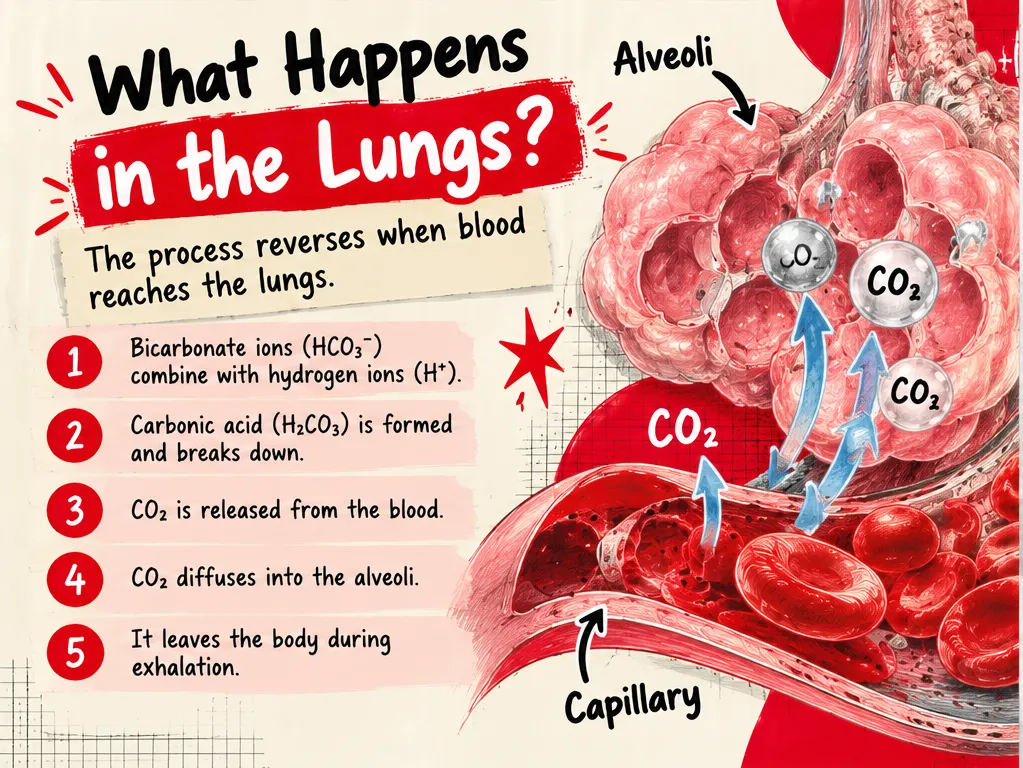
Each of the three forms is unloaded:
- Bicarbonate. Bicarbonate ions in the plasma move back into the red blood cells, swapping places with chloride ions (the chloride shift in reverse).
- Inside the red cell, hydrogen ions and bicarbonate ions join to form carbonic acid, and carbonic anhydrase converts it into carbon dioxide and water.
- Carbaminohaemoglobin. It releases its CO₂, and the haemoglobin is free to pick up oxygen.
- Dissolved CO₂. It diffuses straight from the plasma into the alveoli.
- The carbon dioxide diffuses across the thin respiratory membrane into the alveoli and leaves the body when you breathe out.
The structure of the lungs makes this efficient. The alveoli have very thin walls and are surrounded by capillaries, so the diffusion distance is tiny. For more on that anatomy, see our overview of the human respiratory system.
The Haldane effect: oxygen helps release carbon dioxide
The Haldane effect is named after the physiologist John Scott Haldane. It describes how haemoglobin's ability to carry carbon dioxide depends on whether it is carrying oxygen.
- In the tissues, haemoglobin has released oxygen. Deoxygenated haemoglobin is better at picking up CO₂ (as carbaminohaemoglobin) and at binding hydrogen ions.
- In the lungs, haemoglobin picks up oxygen. Oxygenated haemoglobin binds CO₂ and hydrogen ions less well, so they are pushed off, and the H⁺ recombines with bicarbonate to make CO₂ that can be breathed out.
In short, binding oxygen makes haemoglobin let go of carbon dioxide, and releasing oxygen makes it more willing to take carbon dioxide on. The Haldane effect roughly doubles the amount of carbon dioxide the blood can transport compared with what it could carry without the effect.
It also explains something surprising in the numbers. Carbaminohaemoglobin is only about 20–23% of the total carbon dioxide in blood. Yet when you compare venous blood with arterial blood, so looking only at the carbon dioxide that actually gets loaded and unloaded on each circuit, carbamino compounds account for roughly 30% of the difference, bicarbonate for about 60% and dissolved gas for about 10%. Carbaminohaemoglobin is a small store, but a very active one.
The Bohr effect: carbon dioxide helps release oxygen
The Bohr effect works the other way round. It was first described in 1904 by the Danish physiologist Christian Bohr, whose son was the physicist Niels Bohr. It says that more carbon dioxide, and the lower pH that goes with it, makes haemoglobin let go of oxygen more easily.
Think about a working muscle. It makes extra CO₂ and acid, and the nearby blood becomes more acidic. Haemoglobin's affinity for oxygen falls, so more oxygen is released exactly where it is needed. On an oxygen dissociation graph, this is a shift of the curve to the right.
Haldane effect versus Bohr effect
| Bohr effect | Haldane effect | |
|---|---|---|
| What changes | CO₂ level and pH | Oxygen level (oxygen saturation of haemoglobin) |
| What is affected | How tightly haemoglobin holds oxygen | How much carbon dioxide haemoglobin and the blood can carry |
| In the tissues | High CO₂ and H⁺ make haemoglobin release O₂ | Losing O₂ lets haemoglobin take up more CO₂ and H⁺ |
| In the lungs | Low CO₂ and higher pH help haemoglobin load O₂ | Gaining O₂ makes haemoglobin release CO₂ and H⁺ |
Explain why oxygen is released more readily in an active muscle. (3 marks)
Respiring muscle produces more CO₂, which lowers the pH of the blood. This reduces haemoglobin's affinity for oxygen (the Bohr effect, the curve shifts right), so more oxygen is released to the muscle cells.
Explain why haemoglobin releases CO₂ in the lungs. (2 marks)
Haemoglobin binds oxygen in the lungs, and oxygenated haemoglobin has a lower affinity for CO₂ and H⁺ (the Haldane effect). The partial pressure of CO₂ is also lower in the alveoli, so CO₂ diffuses out.
Carbon dioxide, blood pH and your breathing
Carbon dioxide transport is closely tied to the acidity of the blood. Whenever CO₂ dissolves and reacts with water, it makes carbonic acid and then hydrogen ions. The more carbon dioxide in the blood, the lower (more acidic) the pH. Your body keeps blood pH within a narrow band around 7.4, and carbon dioxide is one of the main things it adjusts to do that.


How your body senses carbon dioxide
You might think that low oxygen is what makes you breathe harder. Normally it is the opposite: the main trigger is a rise in carbon dioxide and hydrogen ion levels. Special receptors called chemoreceptors detect the change:
- Central chemoreceptors in the brain and brainstem respond to rising hydrogen ions, which build up as CO₂ increases.
- Peripheral chemoreceptors in the carotid arteries and the aortic arch also sense changes in blood chemistry.
These receptors signal the respiratory centres in the brainstem, which increase the rate and depth of breathing by making the diaphragm and intercostal muscles contract harder. More air moves in and out, more CO₂ is breathed out, and the blood pH returns towards normal. It is a classic negative feedback loop, a type of control you meet all over homeostasis.
When the balance goes wrong
If the system cannot clear enough carbon dioxide, levels in the blood rise. This is called hypercapnia. For example, slow or shallow breathing (hypoventilation), which can be caused by certain drugs, lung disease or simply holding your breath, causes carbon dioxide and carbonic acid to build up and the blood to become too acidic. That state is respiratory acidosis.
The opposite happens when someone breathes too fast and too deeply, known as hyperventilation. Too much CO₂ is blown off, carbonic acid levels fall, and the blood becomes too alkaline. In both cases the kidneys help over a longer time scale by adjusting how much bicarbonate is kept or lost.
Carbon monoxide: a gas that blocks the carrying system
Do not confuse carbon dioxide with carbon monoxide. Carbon monoxide is a poisonous gas that binds to haemoglobin's haem groups so strongly that oxygen cannot get on, which is why it is dangerous. Carbon dioxide, in contrast, is a normal waste product that attaches elsewhere on the molecule and is released again in the lungs.
Common mistakes to avoid in exams
Examiners see the same slips every year. Check your answers against this list.
- "Most CO₂ is carried dissolved in plasma." No. Most is carried as bicarbonate ions. Dissolved CO₂ is the smallest share, about 7–10%.
- "CO₂ binds to the iron in haemoglobin." No. Oxygen binds to the iron in haem. CO₂ binds to amino groups on the globin chains.
- "Carbonic anhydrase makes the CO₂." No. It is an enzyme that speeds up the reaction between CO₂ and water. It does not create the carbon dioxide, which comes from respiration.
- "Bicarbonate stays inside the red blood cell." No. It moves into the plasma, swapped for chloride ions (the chloride shift).
- "The Bohr and Haldane effects are the same thing." They are mirror images. Bohr describes how CO₂ and pH affect oxygen binding. Haldane describes how oxygen affects CO₂ binding.
- "The lungs make the bicarbonate." No. Most bicarbonate is made in red blood cells in the tissues. In the lungs it is turned back into carbon dioxide.
Where to go next
If you want the gas itself, our page on carbon dioxide gas (CO₂) covers its properties and uses outside the body. To see how other animals move gases and nutrients around, read about animal blood and circulation.
Flip cards: guess the term
Quiz: test yourself
Frequently asked questions about carbon dioxide transport
What is the most common method of carbon dioxide transport in the blood?
The most common method is as bicarbonate (hydrogencarbonate) ions, which carry about 70% of the carbon dioxide. CO₂ reacts with water in red blood cells, helped by the enzyme carbonic anhydrase, to form carbonic acid. This splits into hydrogen ions and bicarbonate, which then move into the plasma.
In what three ways is carbon dioxide transported in the blood?
Carbon dioxide is carried as bicarbonate ions (about 70%), as carbaminohaemoglobin bound to haemoglobin (about 20–23%) and as dissolved gas in the plasma (about 7–10%). Textbooks quote slightly different figures, but bicarbonate is always the largest share and dissolved CO₂ the smallest.
What is carbaminohaemoglobin?
Carbaminohaemoglobin is haemoglobin with carbon dioxide attached. The CO₂ binds to amino groups on the globin protein chains, not to the iron of the haem group where oxygen binds. The reaction is reversible, so the CO₂ is released again in the lungs.
What does carbonic anhydrase do?
Carbonic anhydrase is an enzyme in red blood cells that speeds up the reaction between carbon dioxide and water to form carbonic acid. The carbonic acid then splits into hydrogen and bicarbonate ions. In the lungs the same enzyme speeds up the reverse reaction, which releases carbon dioxide.
What is the chloride shift?
The chloride shift, or Hamburger shift, is the exchange of bicarbonate and chloride ions across the red blood cell membrane. Bicarbonate leaves the cell and chloride enters. Swapping one negative ion for another keeps the electrical charge balanced. It happens in tissue capillaries and reverses in the lungs.
What is the difference between the Haldane effect and the Bohr effect?
The Bohr effect describes how more carbon dioxide and a lower pH make haemoglobin release oxygen more easily. The Haldane effect describes how oxygen levels change carbon dioxide carriage: deoxygenated haemoglobin binds more CO₂ in the tissues, and oxygenated haemoglobin releases it in the lungs.
How is carbon dioxide released in the lungs?
In the lung capillaries, bicarbonate re-enters red cells and combines with hydrogen ions to form carbonic acid, which carbonic anhydrase converts to carbon dioxide and water. Carbaminohaemoglobin also releases CO₂. The gas diffuses into the alveoli, where the partial pressure of CO₂ is lower, and is breathed out.
How does carbon dioxide affect blood pH?
Carbon dioxide reacts with water to form carbonic acid, which releases hydrogen ions, so more CO₂ lowers blood pH and makes it more acidic. Bicarbonate and haemoglobin act as buffers. Breathing out CO₂ raises the pH again, so breathing is a key way the body keeps pH steady around 7.4.
Why does carbon dioxide make you breathe faster?
Rising carbon dioxide increases hydrogen ion levels and lowers blood pH. Chemoreceptors in the brain, carotid arteries and aortic arch detect this and signal the respiratory centres in the brainstem. These increase the rate and depth of breathing, which removes more CO₂ and brings the blood back towards normal.