
New technologies for paralysis rehabilitation try to do one of two jobs: carry movement signals around a damaged part of the nervous system, or make paralysed muscles work with electricity and robotics. They include brain–computer interfaces, robotic exoskeletons, functional electrical stimulation and AI-guided spinal cord stimulation. A few are used in clinics today, but most are still in small research trials.
This article follows the science from the ground up. First, how your brain normally moves a muscle, then what goes wrong in paralysis, then each technology in turn, with the size, date and result of the real studies behind it. None of these technologies is a cure, and we will say so clearly each time.

What is paralysis?
The NHS describes paralysis as being not able to move some or all of your body. It can be temporary or permanent. The NHS lists causes that include stroke or transient ischaemic attack (TIA), head injury, spinal cord injury, Bell’s palsy and multiple sclerosis. Treatment depends on the cause, and support usually includes physiotherapy to build strength, occupational therapy for daily tasks and medicines for pain, stiffness and spasms.
Spinal cord injury is the cause most of these technologies target. The World Health Organization (WHO) estimates that about 15.4 million people were living with a spinal cord injury worldwide in 2021. Most spinal cord injuries are caused by trauma such as falls, road traffic crashes and violence, and the WHO says they are largely preventable. Others come from tumours, degenerative and vascular conditions or infections.
Doctors describe paralysis by which parts of the body are affected:
- Paraplegia affects the legs and lower body.
- Tetraplegia (also called quadriplegia) affects all four limbs and the trunk.
- Hemiplegia affects one side of the body, for example after a stroke.
Scans help the rehabilitation team see where the spine or brain is damaged. That matters because every technology in this article connects to a particular link in the movement chain, and the right choice depends on where the chain is broken.
The science behind it: how your brain moves your body
To see why these technologies exist, you need to know how a movement normally happens. Moving a finger takes just two nerve cells between your brain and the muscle, and the pathway runs like this:
- You decide to move, and the primary motor cortex in the brain starts the command.
- An upper motor neuron carries the signal down the corticospinal tract in the spinal cord.
- It connects, directly or through an interneuron, to a lower motor neuron.
- The axon of the lower motor neuron leaves the spinal cord and travels to the muscle.
- At the neuromuscular junction a chemical signal crosses the gap, and the skeletal muscle contracts.
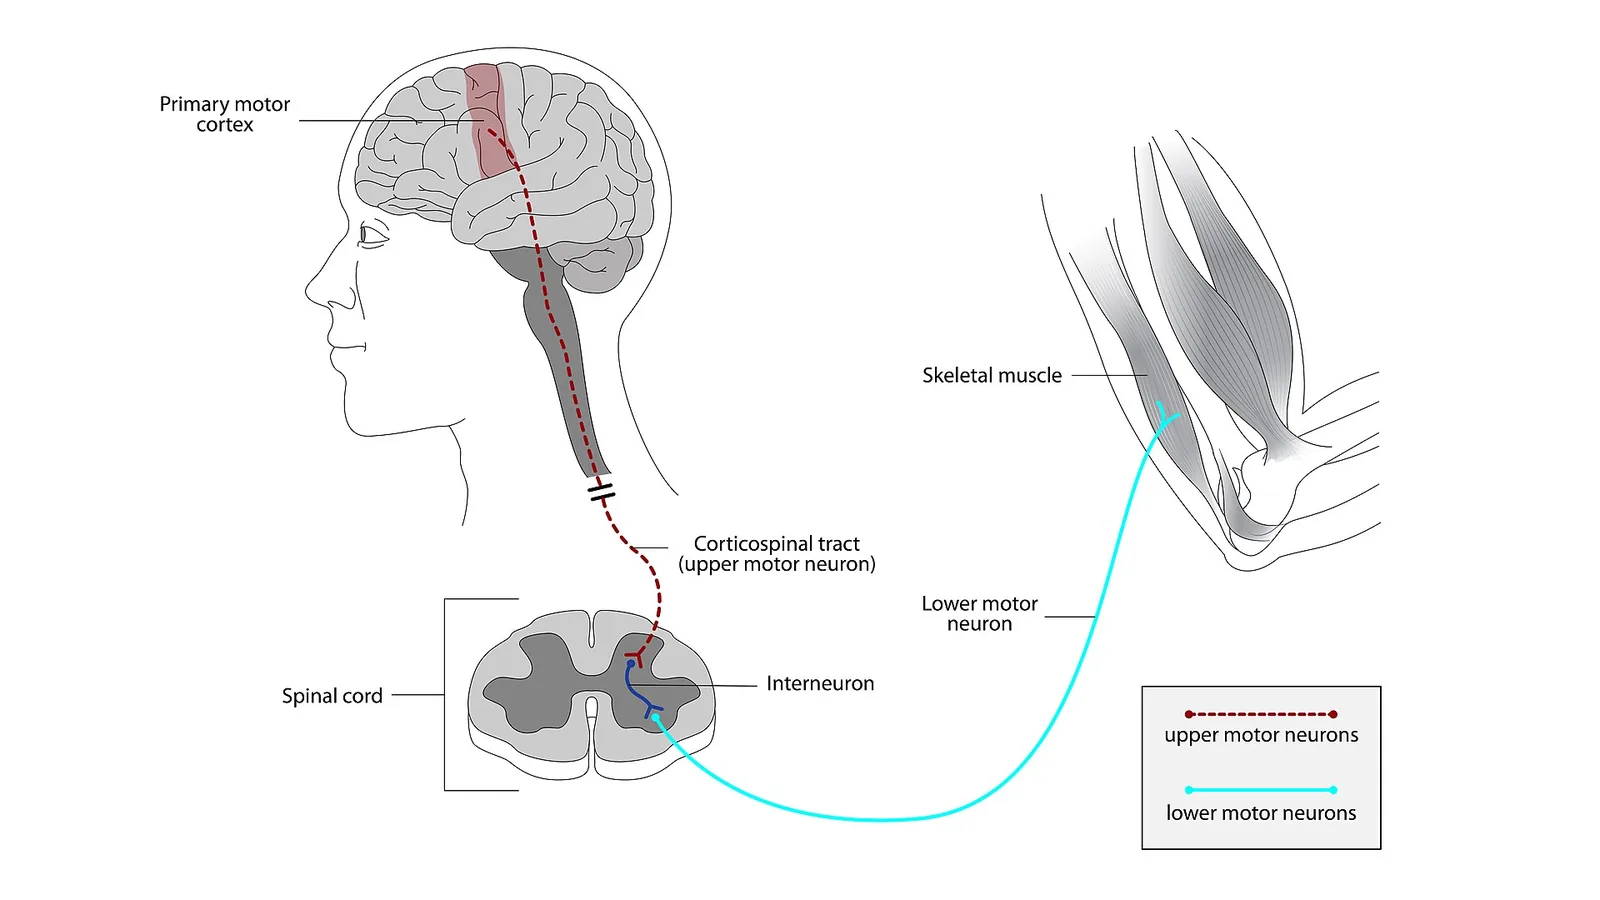
The signal along each neuron is electrical: a travelling impulse called an action potential. Between neurons, and at the muscle, the message is chemical. This is the same electrical-then-chemical pattern you meet in nervous coordination and in the wider study of neuroscience and the brain.
Speed matters too. Neurons wrapped in a fatty myelin sheath conduct impulses much faster, because the impulse jumps between small gaps called nodes of Ranvier. Unmyelinated axons conduct at about 0.5 to 10 metres per second (m/s), while myelinated axons can reach up to 150 m/s. Use the calculator to see the difference. It uses speed = distance ÷ time, rearranged to time = distance ÷ speed.
Try 1.2 m, an example distance from the spinal cord to the foot of an adult, then switch to an unmyelinated fibre.
The answer is a few hundredths of a second, so speed is not the real problem in paralysis. The real problem is that the message cannot get across the injury at all.
What goes wrong in a spinal cord injury
In a spinal cord injury, the damaged section of the cord cannot pass signals along. Commands from the brain stop at the injury, and signals from the body cannot reach the brain. Yet in many injuries the nerve circuits below the damage are still alive. They are simply cut off from the brain.
Research on mice and people supports this idea. In a 2022 study in the journal Nature, electrical stimulation of the spinal cord combined with rehabilitation restored walking in nine people with chronic spinal cord injury. In mice, the researchers identified a group of neurons in the lower spinal cord that are not needed for walking in healthy animals but are needed for recovery after injury. Those same neurons still have to be confirmed in humans, so treat the mouse result as a clue, not a proven human mechanism.
This gives each technology a target:
- Brain to computer: brain–computer interfaces read the brain’s signals directly.
- Legs and hips: exoskeletons move the limbs with motors.
- Nerve to muscle: electrical stimulation triggers the nerve or muscle itself.
- Spinal circuits: spinal cord stimulation wakes up the circuits below the injury.
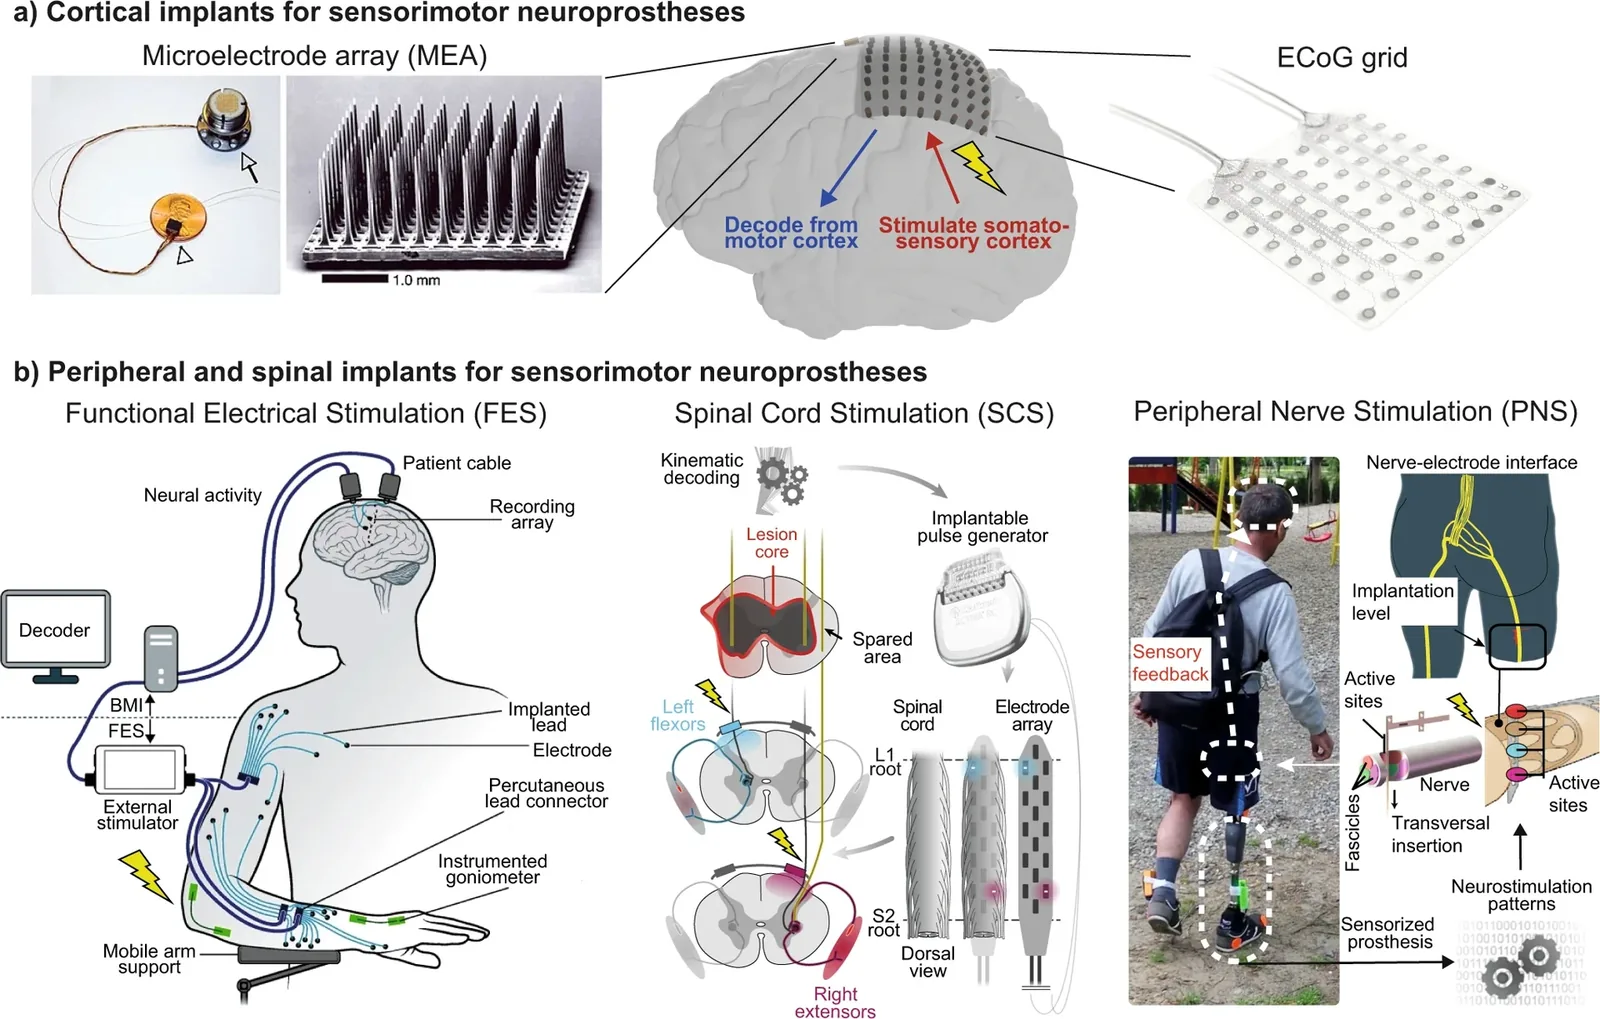
The diagram above, from a 2023 review, shows where each kind of device connects: sensors on or in the brain, stimulators on the muscles and electrodes on the spinal cord and peripheral nerves.
Where each technology stands in 2026
| Technology | Which link it targets | Where it is in 2026 |
|---|---|---|
| Brain–computer interface | Brain to computer or device | Research studies, such as the UK GB-PRIME study and US trials |
| Powered exoskeleton | Hips, knees and legs | FDA allowed marketing in 2014 for some spinal cord injuries; used in some rehabilitation centres |
| Functional electrical stimulation (FES) | Nerve to muscle | NICE has supported it for drop foot since 2009 |
| Spinal cord stimulation | Circuits in the spinal cord | Non-invasive version FDA-authorised in December 2024 for some incomplete neck injuries; implants still in trials |
| Artificial intelligence (AI) | Decoding signals and personalising therapy | Built into several of the technologies above |
Notice the pattern. Only some of these have a regulator’s approval, and the approvals are narrow. The rest of this article explains what each one does and what the evidence shows, starting with the technology that reads the brain directly.
Brain–computer interfaces: turning thoughts into actions
A brain–computer interface (BCI) is a system that records electrical activity from neurons and uses a computer to translate the patterns into commands. The commands can move a cursor, type text, speak with a synthetic voice, drive a robotic arm or trigger a stimulator. The decoder is often a machine-learning program, which is where AI comes in: it learns which pattern of neuron activity matches which intention.
The sensors can sit in three places, and each has a trade-off between signal quality and surgery:
- On the scalp (EEG): no surgery, but the skull blurs and weakens the signals.
- On the surface of the brain (ECoG): a grid or strip of electrodes placed on or over the brain’s surface, which needs an operation but gives clearer signals.
- Inside the brain (intracortical arrays): tiny electrodes, such as the 10 × 10 Utah array, that record from individual neurons.

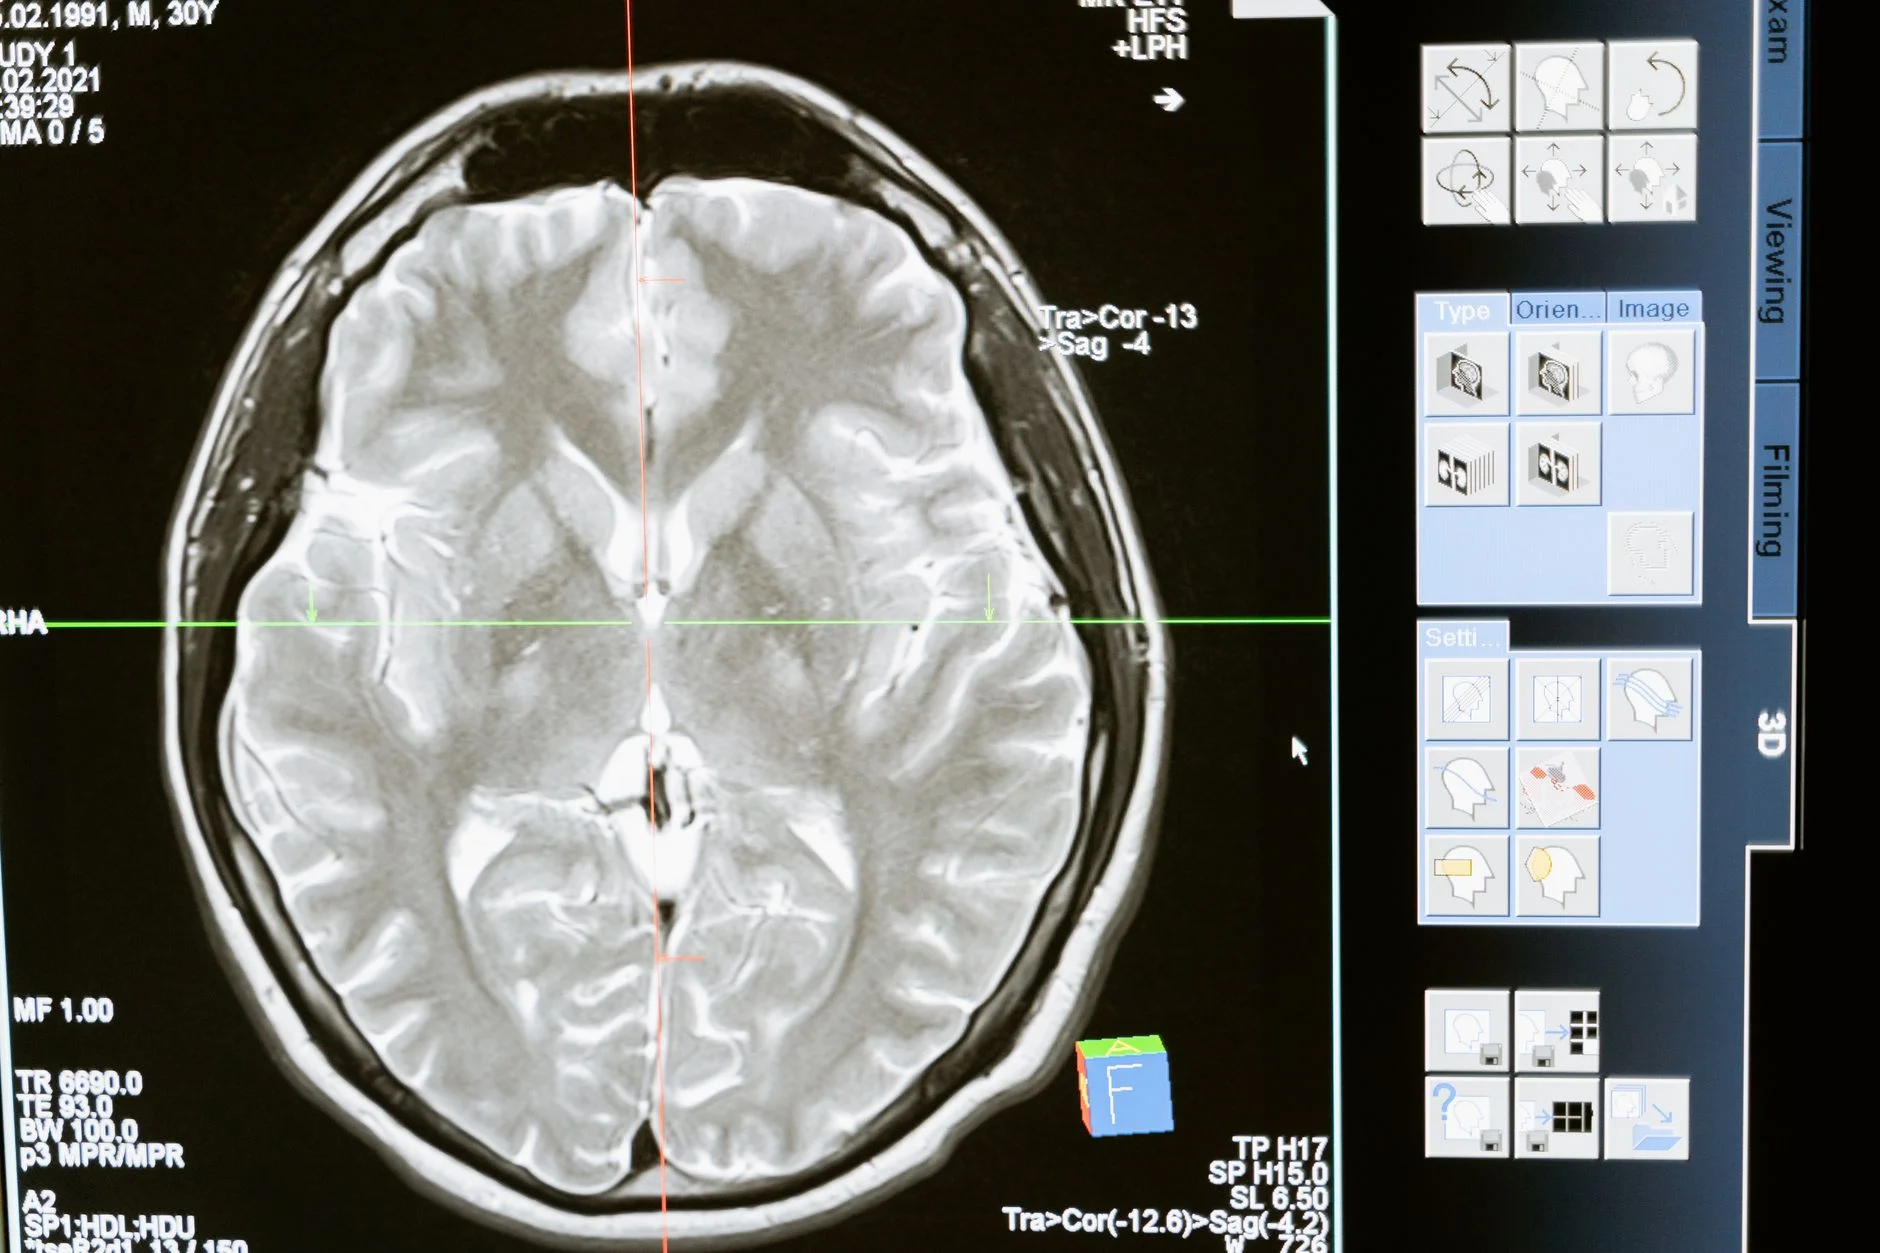
Brain scans such as MRI help surgeons plan where an implant should go. The infographic at the top of this article shows a scalp cap driving a robotic arm. That is a helpful simplification, but the most impressive results so far, including the speech studies below, come from electrodes implanted in the brain.
The UK trial: GB-PRIME at UCLH
The UK’s first Neuralink study is called GB-PRIME. University College London Hospitals NHS Foundation Trust (UCLH) reported on 29 January 2026 that seven patients were taking part. All had surgery at UCLH’s National Hospital for Neurology and Neurosurgery between October and December 2025.
The N1 implant is a fully implantable BCI designed to let people interact with computers through thought. It records through more than 1,000 electrodes spread along ultra-thin threads, finer than a human hair, which a surgical robot places in the brain. The study is meant for people whose paralysis, for example from spinal cord injury or motor neurone disease, stops them using digital devices in the usual way. The aim is to help them control computers, smartphones or tablets.
The study follows trials in the United States and Canada, and the UK version was approved by the MHRA, the Health Research Authority, Health and Care Research Wales and a research ethics committee. It is an early feasibility study, which means it tests safety and function. It is not a treatment you can request, and at the time of writing no GB-PRIME results had been published.
Speech implants: giving people their voice back
The clearest results come from implants that decode speech. In August 2023, researchers reported in Nature a person with motor neurone disease (ALS) who could no longer speak clearly. Her implant decoded attempted speech at 62 words per minute, 3.4 times faster than the previous BCI record. Natural conversation runs at about 160 words per minute. The system made errors, and the word error rate was 9.1% with a 50-word vocabulary and 23.8% with a 125,000-word vocabulary.
A word error rate is the percentage of decoded words that are wrong, so lower is better. A larger vocabulary makes the decoder’s job harder, which is why the second figure is higher.
In August 2024, the New England Journal of Medicine published a study of a 45-year-old man with ALS. Surgeons placed four microelectrode arrays, 256 electrodes in total, in the part of his motor cortex that controls speech. On the first day of use, 25 days after surgery, the system reached 99.6% accuracy on a 50-word vocabulary after just 30 minutes of calibration. On day two it reached 90.2% accuracy on a 125,000-word vocabulary. Over 8.4 months of use, more than 248 hours, accuracy was about 97.5%, at about 32 words per minute in self-paced conversation. The decoded words were spoken by a computer voice built to sound like his voice before ALS.
These are each one person, so no one can say how well the results would carry over to others. Even so, the findings show that the brain’s speech signals can still be read when the muscles can no longer produce clear speech.
Now compare speeds. Pick a pace and see how long a 100-word message would take at each speed. (The calculator was built for timing talks, so ignore its tip about slides.)
A speech implant decodes 62 words per minute. Natural conversation is about 160 words per minute. How many times faster is conversation? (1 mark)
160 ÷ 62 ≈ 2.6, so natural conversation is about 2.6 times faster.
In the 2024 study the system was about 97.5% accurate. How many words would you expect it to get wrong in a 400-word conversation? (2 marks)
The error rate is 100% − 97.5% = 2.5%. Then 0.025 × 400 = 10 words.
What a BCI can and cannot do
A BCI does not repair the spinal cord. Instead it bypasses the damaged route: the signal is read from the brain and sent somewhere else. That “somewhere else” can be a screen, a voice or, as later sections show, a stimulator on the spinal cord. Each use is a different answer to the same question, which is how to get a movement command out of the brain when the normal route is blocked.
Several practical limits are clear from the studies above. An implant needs brain surgery, which carries risk, and today’s systems are used in research settings with researchers close at hand. These are exactly the things that early feasibility studies such as GB-PRIME are designed to find out.
That is why this field moves in careful steps. Small studies check safety first. Larger trials follow only if the early ones go well. Only then does a regulator decide whether a device can be offered to patients as a standard treatment. The next sections cover the technologies that have already made it further along that path.
Robotic exoskeletons: wearable robots for standing and walking
A powered exoskeleton is a wearable frame that fits around the legs and trunk. It has motors at the hips and knees, sensors that detect what the user intends to do, such as a shift of weight or trunk posture, and a battery and computer to control it all. For some people with spinal cord injury, the result is the ability to sit, stand and walk with crutches.

The key idea is feedback. Sensors detect a change in posture, the computer decides which movement the user wants and the motors supply the force at the joints. The exoskeleton therefore does what the weakened muscles cannot, but it still needs the user to start each step.
On 26 June 2014 the US Food and Drug Administration (FDA) allowed marketing of the first motorised exoskeleton for people with lower-body paralysis from spinal cord injury. It was allowed through the De Novo route, which is used for novel devices. The conditions were strict:
- It was for injuries at levels T7 to L5, with T4 to T6 only in rehabilitation institutions.
- Users had to be able to stand with an assistive device, and have hands and shoulders able to use crutches or a walker.
- A trained companion had to assist.
The FDA reviewed clinical data from 30 participants. It also listed risks: pressure sores, bruising and abrasions, falls and injuries, and high blood pressure during use. These are good reminders that a device with regulatory clearance is not risk-free.
What the evidence shows
The best overview is a Cochrane review published on 14 May 2025, covering evidence up to December 2023. It looked at electromechanical and robotic gait-training devices used with physiotherapy after stroke, not spinal cord injury. Its main findings were:
- The devices probably help more people walk independently. This was based on 51 studies with 2,148 people, and works out at about one extra person walking independently for every nine treated.
- They probably do not increase walking speed (73 studies, 3,043 people).
- They do not increase the distance walked in six minutes.
- Benefit may not last at follow-up, and may be most useful in the first three months after stroke.
Cochrane graded the certainty of its main conclusion as moderate, and noted that many of the studies were small or of low quality. Small, low-quality studies can overstate benefits, so results like these should be read with care.
Exoskeletons are mainly rehabilitation and exercise tools. Because users need crutches and, in the FDA’s conditions, a trained companion, they work alongside a wheelchair rather than replacing it.


The carousel is a reminder that rehabilitation is more than high technology. Physiotherapy, wheelchairs and everyday equipment do most of the work today, and the new devices are designed to sit alongside them.
The physics of an exoskeleton
Exoskeletons are a good example of forces at work, covered in Newton’s laws of motion. The motors apply forces, and turning effects called moments, at the hip and knee joints. The frame must support part of the user’s weight, and the weight of the device itself, without tipping. Weight is a force, found from mass and the gravitational field strength.
W = m × g
On Earth g is 9.8 N/kg.
An exoskeleton has a mass of 23 kg (an example value, not a real device). What is its weight on Earth? (g = 9.8 N/kg) (2 marks)
W = m × g = 23 × 9.8 = 225.4 N, which is about 225 N.
Functional electrical stimulation (FES): electricity that moves muscles
Exoskeletons replace the muscles with motors. Functional electrical stimulation (FES) takes the opposite approach and makes the person’s own muscles work. A stimulator sends small, controlled electrical pulses through electrodes, usually on the skin, to a nerve. Each pulse triggers an action potential in the nerve, and the nerve makes the muscle contract.
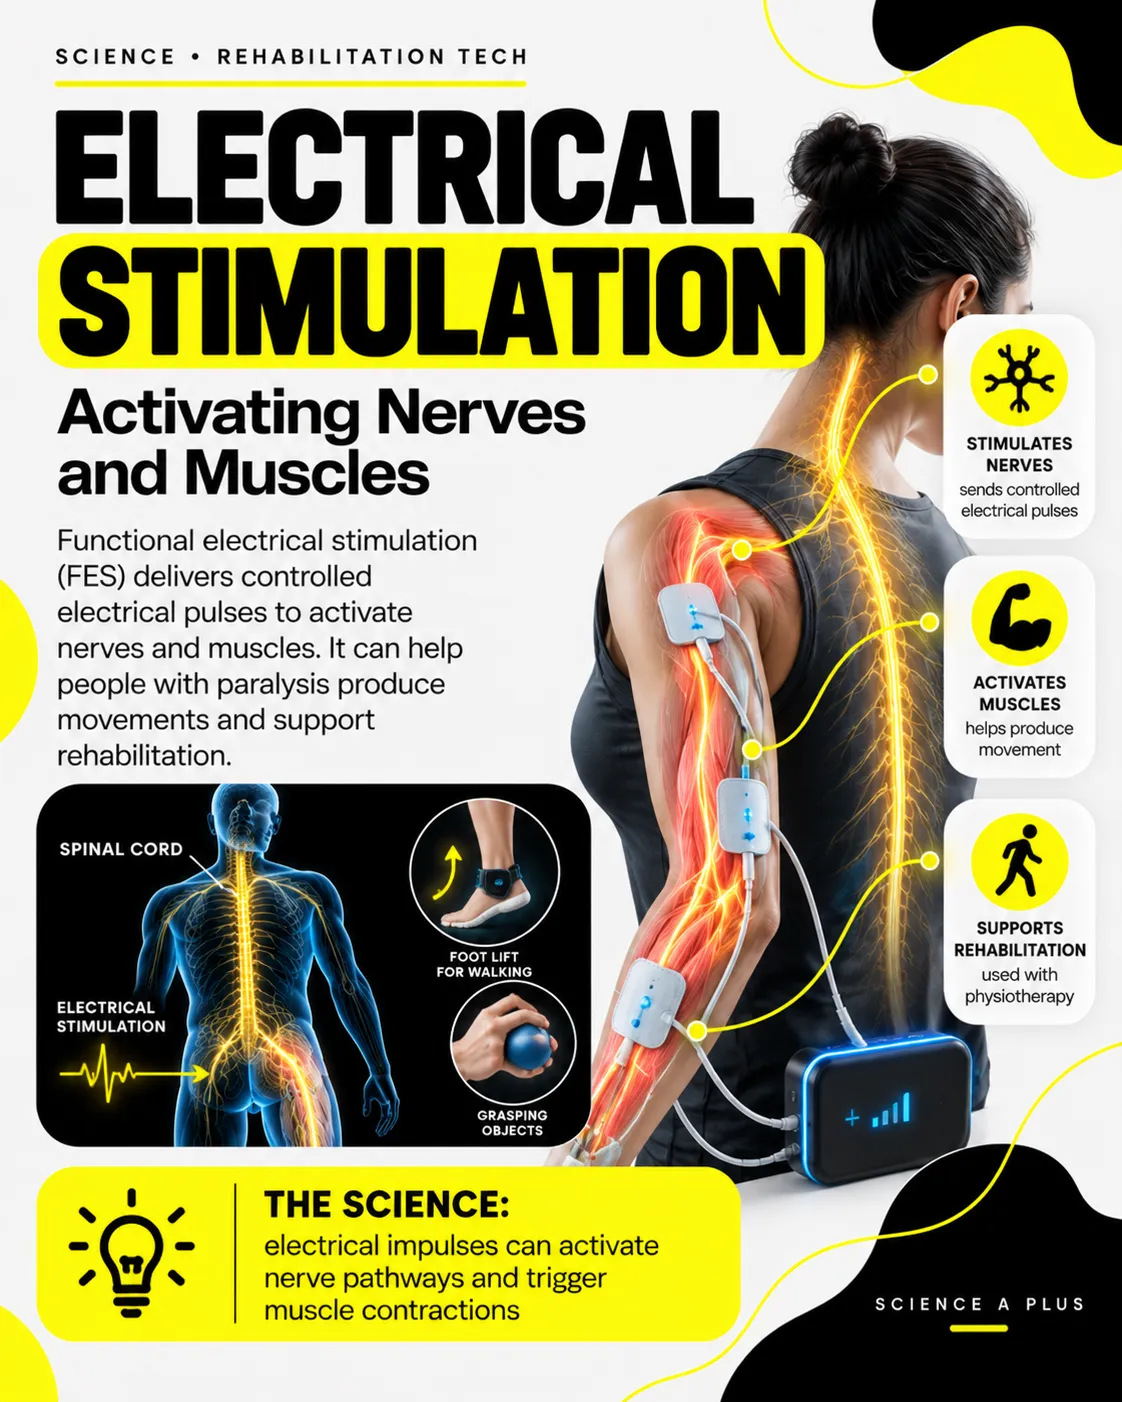
The muscle in question is skeletal muscle, the type that moves your bones, explained in our guide to smooth, skeletal and cardiac muscle. FES is used to lift the foot during walking (known as drop foot), to help with grasping and to power cycling, alongside physiotherapy.
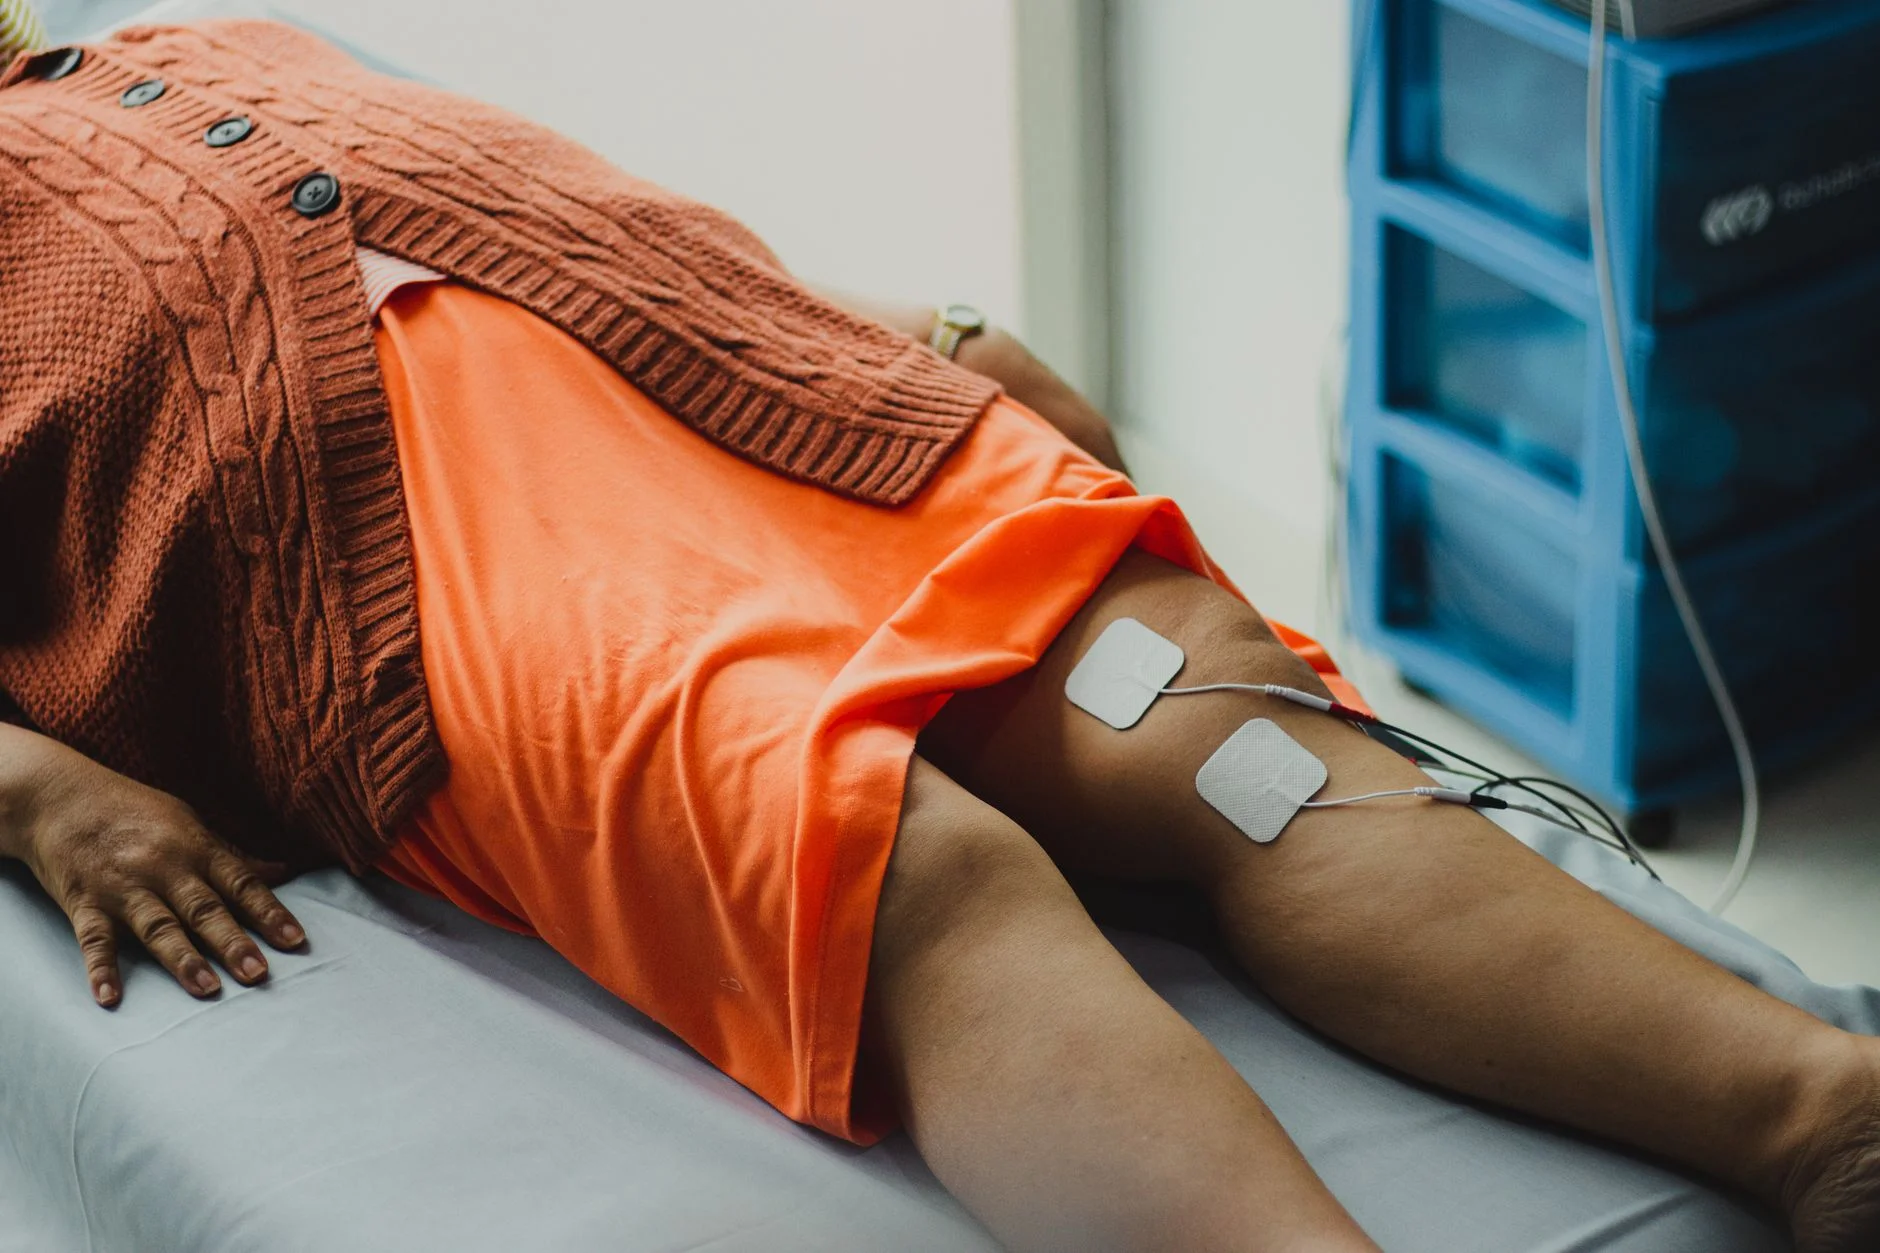
Notice what FES skips. It does not need a message from the brain, because the electrical pulse takes the place of the command. The pulses are timed so that the movement happens at the right moment, for example lifting the foot as the leg swings forward.
FES on the NHS
The National Institute for Health and Care Excellence (NICE) looked at FES for drop foot of central neurological origin in January 2009 (guidance IPG278). It concluded that the evidence on safety and efficacy, meaning whether it improves gait, was adequate to support use with normal arrangements for clinical governance, consent and audit. Patients for implanted FES should be chosen by a multidisciplinary rehabilitation team.
NICE also says FES is not normally suitable for people with lower motor neurone lesions. This follows from the science in the first section: FES stimulates the nerve, so the lower motor neuron and the muscle must be intact.
Access depends on where you live. NHS funding is decided by each local Integrated Care Board (ICB). For example, the Humber and North Yorkshire ICB funds skin-surface FES after review by a local multidisciplinary team, while the Derby and Derbyshire policy does not routinely commission the wired skin-surface version.
FES works at the nerve and muscle. The next technologies work higher up, at the spinal cord and brain, and combine all the ideas so far.
AI-powered rehabilitation: reconnecting the brain and spinal cord
The newest approaches join the ideas from earlier sections into one loop. Artificial intelligence (AI) software reads brain or movement signals, works out what the person intends and tells a stimulator to activate the right spinal circuits at the right moment. The infographic below shows the four steps in order.

- Brain signals: electrodes record the intention to move.
- AI interprets: the decoder turns the pattern into a command.
- Stimulation: electrical pulses activate circuits in the spinal cord.
- Movement: the muscles contract.
AI has three jobs in this loop: decoding brain and movement signals, timing the stimulation to match the movement and adapting therapy to how a person is progressing. The card itself ends with an honest warning: “These technologies are at different stages of development… They do not guarantee a complete cure for paralysis.” Keep that in mind through the rest of this section.
Spinal cord stimulation
In epidural stimulation, a row of electrodes sits on the outside of the spinal cord’s protective covering and delivers electrical pulses. Two 2022 studies show what it can do. In Nature Medicine, Rowald and colleagues described three people with complete sensorimotor paralysis after spinal cord injury. A new paddle-shaped electrode array on the lower spinal cord, targeting the dorsal roots, ran activity-specific stimulation programmes. Within a single day, with support and training, they could stand, walk, cycle, swim and control their trunk.
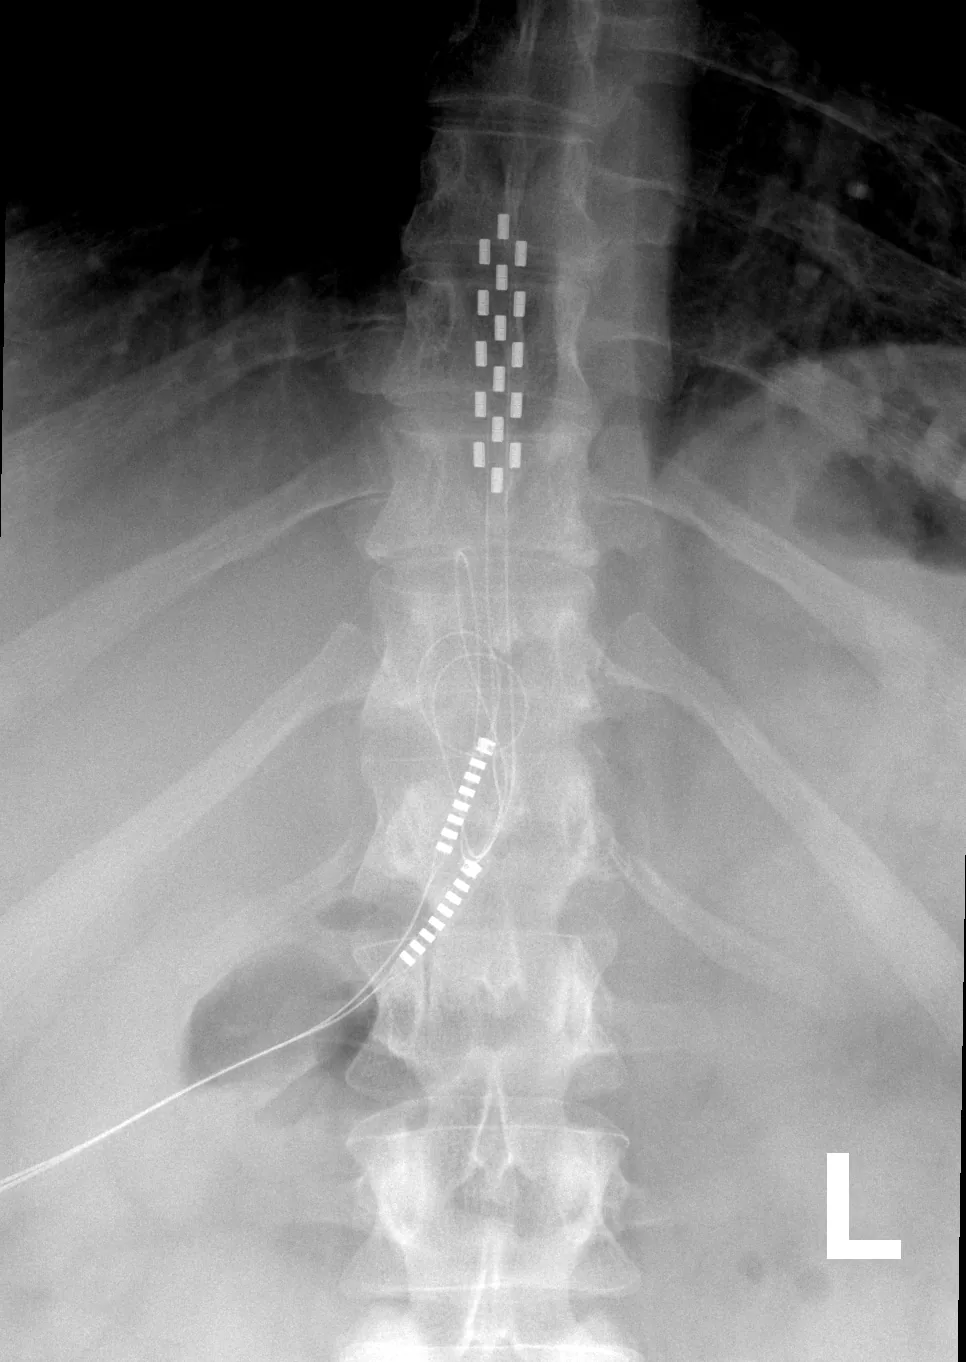
In Nature, Kathe and colleagues reported nine people with chronic spinal cord injury who regained walking with epidural stimulation and rehabilitation. The mouse experiments in the same paper identified the spinal neurons described earlier. Spinal cord circuits can produce movement patterns on their own, a bit like the circuits in a reflex arc, so stimulation may be waking circuits that were always there.
A “digital bridge”: the brain–spine interface
In 2023, Nature published a study of one man, Gert-Jan, who has chronic tetraplegia after a cycling accident. Implants over his brain read his movement intention, and AI decoding drove wireless epidural stimulation of his spinal cord. This link is called a brain–spine interface, or digital bridge.
The system was calibrated within a few minutes and stayed reliable for over a year, including use at home. He could stand, walk, climb stairs and cross complex terrain. He also regained some walking with crutches even when the system was switched off, which suggests some neurological recovery. It is still the result of one man in one study.
Non-invasive stimulation: the Up-LIFT trial
Not all spinal stimulation needs surgery. In the Up-LIFT trial, published in Nature Medicine in 2024, 60 people with chronic neck (cervical) spinal cord injury completed the study at 14 sites in North America and Europe. Electrodes on the skin over the neck stimulated spinal circuits during rehabilitation. Compared with rehabilitation alone, 72% of participants improved beyond the minimal important difference in both strength and function, and 90% did in strength or function. There were no serious adverse events related to the therapy.
There was no sham control group, because all participants received the therapy and knew it, so results can overstate the benefit. Even so, on 19 December 2024 the FDA granted De Novo authorisation to the ARC-EX system. It is for adults aged 18 to 75 with chronic, non-progressive deficits from incomplete spinal cord injury at levels C2 to C8, to improve hand strength and sensation, and it is used in clinics. The FDA noted that the device does not show neurological recovery on the ASIA scale.
Hype or hope? How to read a paralysis-technology headline
Headlines about “paralysed man walks again” are real stories, but they leave out the details that matter. Research studies come in stages. Feasibility studies are tiny and check safety. Pivotal trials are larger and help decide regulatory approval. Randomised controlled trials, with a control or sham group, are the strongest evidence, whereas single-arm open-label trials can overstate benefit. Use this checklist on any headline.
- How many people were in the study?
- Was there a control or sham group?
- Was it a feasibility study or a pivotal trial?
- How long were people followed up?
- Is it approved by a regulator such as the FDA or MHRA, and is it used in the NHS?
Every device here works by starting or reading action potentials. Future electrodes and materials may borrow from nanotechnology in medicine, but that is for the future, not a claim about today.
Which technology?
Frequently asked questions about new technologies for paralysis
What new technologies are used for paralysis rehabilitation?
The main ones are brain–computer interfaces, powered exoskeletons, functional electrical stimulation (FES) and spinal cord stimulation, often guided by AI software. Some, such as FES for drop foot, are established in the NHS. Many others, including implanted brain interfaces, are still in research studies.
Can paralysis be cured with new technology?
No technology currently cures paralysis. Some people in small trials have regained movement or communication with devices, and a few kept some recovery when the device was off. These are early results, usually in a handful of people, so they should not be treated as a guaranteed outcome.
How does a brain–computer interface work?
Sensors record electrical activity from neurons, either from the scalp, from the brain’s surface or from electrodes inside the brain. A computer program, often using machine learning, decodes the patterns into commands. These can control a cursor, text, a voice or a stimulator.
Is the Neuralink brain implant being tested in the UK?
Yes. The GB-PRIME study at University College London Hospitals reported seven patients in January 2026, all operated on between October and December 2025. It is an early feasibility study of safety and function, approved by the MHRA, and it is not a treatment people can request.
Can a robotic exoskeleton help a paralysed person walk?
For some people with spinal cord injury, a powered exoskeleton lets them stand and walk with crutches and a trained companion. The FDA allowed the first one in 2014, with limits on injury level. Users still need rehabilitation support, and exoskeletons work alongside a wheelchair.
What is functional electrical stimulation, and is it available on the NHS?
FES uses small electrical pulses, usually through skin electrodes, to make a nerve trigger a muscle contraction, such as lifting the foot in drop foot. NICE supported it in 2009, but local funding varies between Integrated Care Boards, so ask a rehabilitation team.
What is spinal cord stimulation for paralysis?
It delivers electrical pulses to the spinal cord, either through implanted electrodes or through electrodes on the skin. The aim is to wake up spinal circuits below an injury during rehabilitation. In trials, it helped some people stand, walk or improve hand strength.
Can people with a complete spinal cord injury walk again?
A few people in small trials have stood, stepped or walked with stimulation and support. In 2022 three people did so using a spinal implant, and in 2023 one man with an incomplete (partial) injury did with a brain–spine interface. These are research results, not a standard treatment.
Who should I talk to about rehabilitation technology?
Start with your GP or your rehabilitation team, including the physiotherapist, occupational therapist and consultant. They can say which options suit your injury. Call 999 for sudden weakness or paralysis, or if it follows a head, neck or back injury.



